
ISO 13485:2016 · CE Marked under EU MDR 2017/745 · Exporting to 25+ Countries +91 9266125395 [email protected]
Surgeine Healthcare logo
0%

Choosing Sterile Surgical Drapes in 2026 requires more than comparing price, fabric weight, or packaging. The decision begins with procedure-specific risk. A cardiac operation, orthopedic implant case, and short outpatient procedure create different fluid, pressure, and movement challenges. WHO’s Global Guidelines for the Prevention of Surgical Site Infection report that surgical-site infections affect approximately 11% of surgical patients in low- and middle-income countries. The burden is serious. The drape is not a decorative layer.

AAMI PB70 classifies surgical gowns and drapes by liquid-barrier performance, from Level 1 to Level 4. That framework helps purchasing teams match protection with exposure risk. CDC guidance also emphasizes aseptic technique, sterile-field control, and appropriate protective barriers. Recent market analyses from Grand View Research and Fortune Business Insights indicate continued growth in the surgical drapes and gowns sector, driven by infection-prevention programs, hospital expansion, and demand for disposable products. Market growth, however, does not prove clinical superiority.

Dr. William A. Rutala, a widely cited infection-prevention expert, summarizes the core principle: “The goal is to prevent contamination.” That principle should guide every specification. Evaluate absorbency, lint release, tensile strength, conformability, adhesive performance, packaging integrity, and sterilization validation. Check real workflow conditions. A technically compliant drape can still fail when it shifts, tears, or obstructs access. No checklist replaces judgment. This guide examines evidence, standards, supplier transparency, and practical handling details, while acknowledging an uncomfortable truth: selecting the cheapest Sterile Surgical Drapes may create costs that appear only after the procedure.
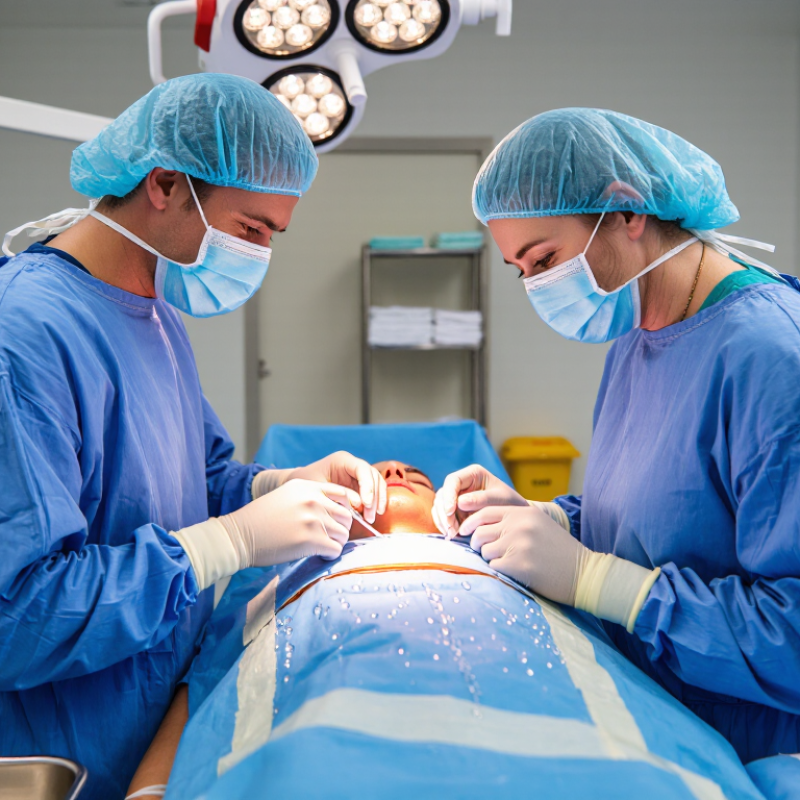
How to Choose Sterile Surgical Drapes in 2026?

Define Surgical Drapes by Risk Using the CDC’s 2–5% SSI Benchmark

How to Choose Sterile Surgical Drapes in 2026?

Define the drape by infection risk, not by the operation’s name. The CDC does not set one universal 2–5% SSI cutoff for every procedure. However, this range can support local risk discussions when paired with reliable surveillance data. A facility should compare its current SSI rate with procedure-specific results, patient factors, and wound classifications. Numbers alone can mislead.

For lower-risk procedures, choose sterile drapes that maintain a stable field and prevent edge migration. For higher-risk cases, assess fluid resistance, absorbency, adhesive performance, and coverage around the incision. Large abdominal procedures may require reinforced areas where irrigation fluid collects. Orthopedic cases need careful control of pooling and fabric lint. Movement matters too. A loose fenestration can expose the incision during repositioning.

In practice, I would review three details before approval: the expected fluid volume, operative duration, and staff contact around the field.

Drapes should remain intact without tearing during normal handling. Packaging must be dry, sealed, and traceable. That sounds basic. It is often overlooked.

A 2–5% SSI signal should trigger investigation, not automatic product replacement. Review hand preparation, antibiotic timing, room traffic, instrument handling, and drape placement together. The drape may be involved, but it may not be the main cause. Local audit results should refine the selection over time. Perfect risk prediction is unrealistic. Careful reassessment is practical.

Match Barrier Performance to AAMI PB70 Levels 1–4 and EN 13795 Classes

How to Choose Sterile Surgical Drapes in 2026?

Choosing surgical drapes starts with fluid exposure, not price or fabric weight. AAMI PB70 Level 1 suits procedures with minimal fluid contact. Level 2 handles low fluid exposure. Level 3 provides stronger resistance during moderate bleeding or irrigation. Level 4 is designed for heavy fluid contact and bloodborne pathogen protection. These levels describe barrier performance, but they do not replace procedure-specific risk assessment.

EN 13795 uses different requirements and should not be treated as a direct translation of AAMI levels. Check whether the drape meets standard or high-performance requirements for liquid penetration, cleanliness, linting, and microbial barrier performance. Review test reports, product specifications, and sterile-pack integrity. A neat comparison chart can still mislead. Testing conditions may differ from the wet, folded, and stretched conditions found in an operating room.

Tips: Match Level 1 or 2 with short, low-fluid procedures. Consider Level 3 for orthopedic irrigation or prolonged operations. Select Level 4 when fluid volume and contamination risk are substantial. Confirm the EN 13795 classification separately. Inspect packaging before use. Small tears matter. Also check drape size, fenestration placement, absorbent zones, and securement points. Staff feedback is useful, although it is not a substitute for documented performance evidence. Some selections will need revision after real procedure audits.

Compare SMS, Spunlace, and Plastic Laminates by Fluid-Resistance Data

How to Choose Sterile Surgical Drapes in 2026?

Choosing sterile surgical drapes in 2026 starts with fluid-resistance evidence, not fabric labels. SMS, spunlace, and plastic laminates behave differently under pressure, splash, and prolonged contact.

ANSI/AAMI PB70:2022 defines graded barrier levels. Its hydrostatic thresholds include 20 cm H₂O for Level 2 and 50 cm H₂O for Level 3. Level 4 requires ASTM F1671 viral-penetration testing. These figures make “waterproof” an incomplete purchasing claim.

SMS usually balances air permeability, strength, and moderate fluid protection. Spunlace feels softer and absorbs efficiently, but exposed liquid may migrate through seams.

Plastic-laminated structures often provide the strongest continuous barrier. However, they can trap heat and increase condensation.

ASTM F1670 measures synthetic-blood penetration, while ASTM F1671 uses a bacteriophage challenge. Passing one test does not prove performance in every procedure. EN 13795 also considers wet microbial penetration, lint, and cleanliness.

A practical evaluation may reveal slippery surfaces or poor drape movement. That trade-off deserves honest review.

Tips: Match the drape to fluid volume, procedure length, and pressure. Request lot-specific hydrostatic results, seam data, and ASTM test reports. Check performance after sterilization and folding. Test samples under light and heavy splash. Do not select by GSM alone. My own weak assumption would be equating plastic film with better safety; comfort, adhesion, and movement can still undermine coverage.

Verify Sterility, Packaging, and ISO 11607 Shelf-Life Requirements

How to Choose Sterile Surgical Drapes in 2026?

Sterile surgical drapes should arrive with an intact sterile barrier, clear labeling, and traceable lot information. Do not trust appearance alone. A clean pouch can still contain a damaged seal or a tiny puncture. Check the expiration date, sterilization method, package configuration, and instructions for use. The label should support quick verification before opening. If information is missing, quarantine the pack and ask the supplier for documented clarification.

ISO 11607 requires packaging systems for terminally sterilized medical devices to be designed, tested, and validated. For surgical drapes, review evidence for seal strength, package integrity, and simulated transport. Shelf life should reflect real-time or accelerated aging, followed by integrity testing. Distribution testing matters too. A package surviving storage may fail after vibration, compression, or humidity exposure. Look for documented validation, not a simple “sterile until” statement. This is where purchasing decisions can become too optimistic.

Tips: Inspect every pouch under good lighting. Feel for moisture, crushed edges, and loose seals. Match the lot number with receiving records. Never open a questionable pack. Store cartons off the floor, away from heat and moisture. Keep older validated stock accessible. A small gap is easy to miss. That deserves a second look. When evidence is incomplete, pausing the procedure supply is safer than guessing.

Balance Clinical Fit, Waste, and Total Cost per Procedure in 2026

How to Choose Sterile Surgical Drapes in 2026?

Choosing sterile surgical drapes now requires more than checking barrier performance. Start with the procedure. A laparotomy needs different fenestration, fluid control, and adhesive behavior than a short arthroscopy. During evaluations, observe real setup time, packaging waste, folding effort, and drape movement around the wound. Small handling problems can create delays and extra opening of supplies.

Calculate total cost per procedure, not unit price. Include purchasing, storage, staff labor, waste treatment, and replacement caused by tearing or poor fit.

The World Health Organization reports that about 85% of healthcare waste is generally non-hazardous, while 15% is hazardous (WHO, Health-care Waste Fact Sheet, 2024).

Better segregation depends on clear design and trained staff. A drape that reduces unnecessary contamination may lower disposal volume, but the result must be measured locally.

Our first estimate was too optimistic.

Request documented testing for liquid resistance, microbial barrier performance, linting, and packaging integrity. Review evidence against recognized perioperative guidance, including AORN’s Guidelines for Perioperative Practice.

Compare single-use and reusable options through a life-cycle assessment, not assumptions. The Sustainable Healthcare Coalition warns that environmental impact depends on materials, manufacturing, transport, use, and end-of-life treatment (Sustainable Healthcare Coalition, 2023).

Track waste weight, opening time, defect rates, and cost across several procedures. One month is rarely enough.

A practical trial may reveal uncomfortable trade-offs.

FAQS

How should surgical drapes be selected for different infection risks?

Choose them by fluid exposure, wound classification, and movement risk—not by the operation’s name. Numbers can mislead. Review local infection data and patient factors together.

What should be checked during lower-risk procedures?

Use a sterile drape that keeps the field stable and prevents edge migration. Check the fenestration during repositioning. A loose opening can expose the incision.

Which drape features matter during high-fluid procedures?

Assess fluid resistance, absorbency, adhesive performance, and incision coverage. Reinforced areas may help when irrigation fluid collects. Pooling requires careful control.

How do AAMI PB70 Levels 1–4 guide selection?

Level 1 suits minimal fluid exposure. Level 2 handles low exposure. Level 3 supports moderate bleeding or irrigation. Level 4 fits heavy fluid contact and higher contamination concerns.

Can EN 13795 classes be directly matched with AAMI PB70 levels?

No. They use different requirements. Check liquid penetration, cleanliness, linting, and microbial barrier evidence separately. A comparison chart may oversimplify testing conditions.

What practical details should staff review before approving a drape?

Review expected fluid volume, procedure duration, and staff contact around the field. Confirm the drape remains intact during normal handling. This sounds basic. It is often missed.

What should be inspected before opening a sterile drape package?

Check the seal, expiration date, sterilization information, lot number, and package condition. Look under good lighting. Feel for moisture, crushed edges, and loose seals.

What should happen when a package has unclear or damaged information?

Quarantine the pack and request documented clarification. Do not open a questionable package. A tiny puncture matters. Guessing is not a safe supply strategy.

How should shelf life and transport damage be evaluated?

Review packaging validation, seal strength, integrity testing, aging evidence, and simulated transport results. Vibration, compression, and humidity can damage stored packs.

Does a 2–5% SSI signal prove that the drape caused infections?

No. It should trigger investigation, not automatic replacement. Review hand preparation, antibiotic timing, room traffic, instruments, and placement together. The drape may not be the main cause.

Conclusion

Choosing Sterile Surgical Drapes in 2026 requires a risk-based approach rather than relying on price or appearance alone. Start by assessing the procedure, fluid exposure, and infection-prevention goals, using the CDC’s 2–5% surgical-site infection benchmark as a planning reference. Then match barrier performance to the appropriate AAMI PB70 Level 1–4 and EN 13795 class, ensuring the drape can manage expected moisture, pressure, and handling conditions.

Material selection should be supported by measurable fluid-resistance data. SMS, spunlace, and plastic-laminated constructions each offer different combinations of protection, flexibility, breathability, and comfort. Buyers should also verify sterility assurance, package integrity, labeling, and shelf-life documentation in line with ISO 11607 requirements. Finally, evaluate clinical fit, setup efficiency, waste volume, and total cost per procedure. The best Sterile Surgical Drapes provide dependable protection while supporting practical workflow, responsible resource use, and consistent surgical performance.

Amelia

Amelia

Amelia is a professional marketing specialist dedicated to helping businesses understand products, markets, and customer needs through clear, practical, and insightful communication. With extensive knowledge of the company’s products and services, she regularly contributes expert articles to the......